
Summary
We support:
- Converting Medicare, Medicaid, and the ACA into fixed, real, per-capita subsidies
- Enforcing a universal mandate for insurance coverage with meaningful penalties
- Using significant co-pays and deductibles to encourage cost control
- Adjusting premiums over time to maintain fixed per-capita costs
- Adjusting Medicaid compensation and coverage to maintain cost discipline
If you have already made up your mind, then scroll to the bottom of the page and take the poll to let us know how you feel. If you need to hear more, please read the background section below.
Curious how your views compare? Early input has a meaningful impact—vote below (scroll down) to see the current results.
Your input helps us refine these policy positions.
Background
Problems with the Current Health Care System
There are a number of interrelated factors behind the interest in health care as a public policy issue. To some, the principal problem is that a significant number of people remain uninsured. To others, the problem is that the costs of Medicare and Medicaid, and health care in general, are rising far more rapidly than overall inflation.
Health Care and Insurance
Medical care expenses can be very large in the face of a serious accident or illness. As medical science continues to make progress, the expense of treating patients rises because there is more that can be done. However, the cost of medical care also rises, in part, because society subsidizes medical care expenditures, causing the demand for them to be very unresponsive to price. As with other potentially catastrophic events, a system of insurance has grown up to handle medical care expenditures. This system includes employer-provided policies, private individual policies, Medicare, Medicaid, and the Affordable Care Act (ObamaCare).
Most of these forms of health care insurance have relatively low deductibles and co-pays. Low deductibles and co-pays shield patients from the true costs of their care and make them indifferent to its cost. The co-pays and deductibles built into Medicare are largely undone by Medicare Supplement and Medicare Advantage Plans, which convert Medicare into a low co-pay, low deductibles system.
The prevalence of health care insurance through employers is, partly, due to the fact that, unlike other employee benefits, health care benefits are not a taxable benefit for the employee. This encourages employers to compensate employees, as much as possible, through generous health care benefits, with low co-pays and deductibles, in lieu of higher, taxable, wages. Because most insured individuals receive their health insurance through their employers, there is also a concern about the lack of portability of health insurance. Those with employer-provided coverage fear losing their coverage, when changing jobs, and fear being unable to re-establish it because of pre-existing conditions.
Health Care and the Uninsured
Eleven percent of non-elderly Americans aren’t covered by any kind of health care insurance. (This number was over 18% prior to ObamaCare. Much, if not most, of the reduction in the uninsured was due to the expansion of Medicaid.) As a society we are unwilling to let people go without urgently needed medical care, so we provide emergency room care to all who come and, if the patient cannot pay, the costs of that care are absorbed by the hospital and passed on to other patients and their insurers. This turns out to be an expensive and inefficient way to provide medical care to the uninsured. It also encourages the uninsured to ignore medical problems until they reach crisis levels and are more expensive to treat. In a kind of vicious cycle, the high cost of insurance provides an incentive for individuals to accept the risk of going without insurance, thereby shifting additional costs for catastrophic care, for these individuals, back onto the insured, further driving up the cost of insurance.
A key concept of the ACA, as originally conceived, was an individual mandate to maintain health insurance backed by a tax penalty for those who did not comply. As enacted, the penalty was far too low and even that penalty was eliminated in 2018. This, largely, explains why the principal impact of the ACA, on increasing the percentage insured, was through the expansion of Medicaid.
Summary of the Efficiency Problems and the Issue of Equity
Because of all of these factors, the cost of health care is rising so fast that it threatens the ability of government to provide benefits, like Medicare and Medicaid, at anything like current levels. The rapid rate of increase in medical care costs also raises concerns among individuals and employers who provide health care coverage about their ability to pay for medical care insurance in the long run. Some of this increase in cost is the consequence of better care being technologically possible. Were it not for the fact that we are subsidizing health care, these increases in cost due to technological change would not be a public policy issue. But some of this increase in cost is due to inefficiencies in the way we have decided to pay for medical care. Much of this inefficiency is driven by earlier, well intended, public policy decisions and we can change public policy to reduce or eliminate these inefficiencies.
These inefficiencies, while they are serious, do not constitute the whole of the motivation behind those who want to change how health care is provided in the U.S. For many people, they are not even the major concern.
Health Care as a Right
Some people believe that health care is a right and ought not to be allocated or rationed through any kind of market system. For a variety of reasons, we feel that it is unhelpful to characterize any good or service as a “right,” even if it makes good public policy sense to subsidize or provide that service publicly. Doing so only inflames the anger of those who are expected to pay for the “right” and creates expectations, among those who feel entitled to it, that may be economically impossible to fulfill.
Labeling health care as a right is also problematic because “health care” is not a well defined thing. Do those who support “free health care for all’ mean all forms of health care including dental, vision, podiatry, psychiatric care, massage therapy, acupuncture, etc.? The slope here is very slippery and exceedingly costly. That being said, we feel that there are valid public policy reasons to subsidize some level of health care for all U.S. citizens and legal residents, not just the elderly, the indigent, and the disabled. Among these reasons are: public health concerns about communicable diseases like tuberculosis and the recent Covid-19 pandemic; the relationship between health, learning, productivity, and employability; and the fact that we will provide health care to desperately ill individuals anyway (and it is better to provide this care when it is less expensive and more effective). In addition, providing a base level of health care insurance for everyone strikes us as a better way to promote long-term social mobility and income equality than outright transfer payments.
Problems with the Affordable Health Care Act, “ObamaCare”
There is very little in the Act that attempts to make health care more affordable, except for those who are subsidized. Expanding employer-provided health care only exacerbates the problems associated with providing health care through employment. In addition, because the Act provided very low penalties (now zero) for failure to get insurance and requires insurers to accept all applicants regardless of pre-existing conditions, it creates incentives for individuals to behave strategically within the system. This was supposed to be the point of the individual mandate. However, in order to make the mandate politically palatable, Congress stripped the mandate of its teeth, with a very low penalty for non-compliance, and undermined the effectiveness of the system. The decision, on the part of Congress in 2017, to strip the act of any penalty for violating the individual mandate only makes this problem worse. It is likely, in our view, that the reason behind eliminating the penalty for violating the individual mandate was to contribute to the system’s eventual failure.
The Role for the States in Health Care Policy
With a number of issues, we propose letting the states take action first rather than jumping in with a federal solution. Generally, this is a good approach. It is in harmony with the Constitutional principle of delegating powers to the states. In addition, it has the advantage of allowing state level experiments to determine which public policy prescription works best, without committing the whole nation to one direction. Unfortunately, in this case, federal tax and entitlement policies are at the root of the problems with the current health care system. In addition, separate regulatory structures on this issue will mean a fragmented, less efficient, and less competitive health insurance industry.
Universal Health Insurance and Medicare for All
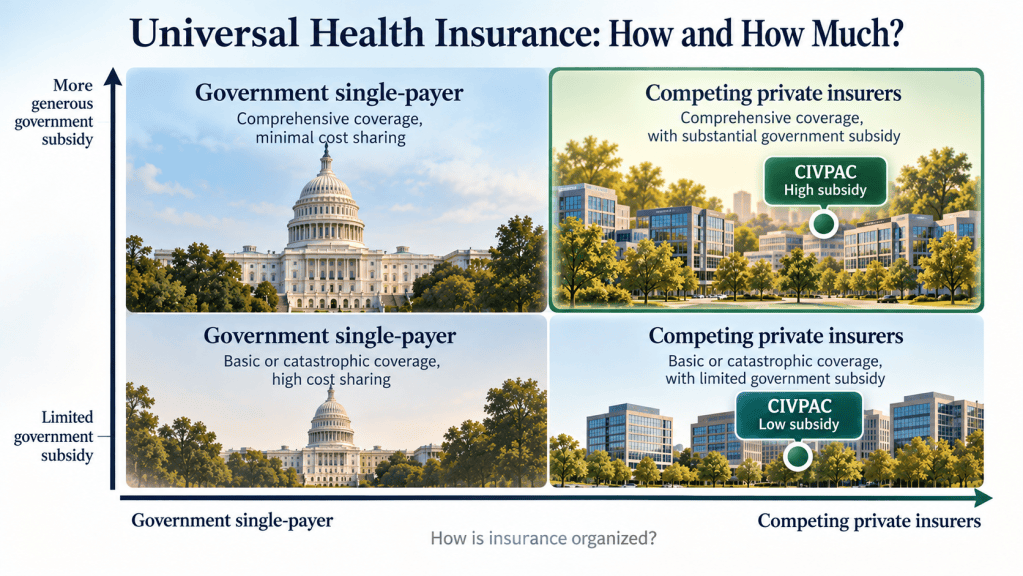
The name “Medicare for All” is misleading. It suggests simply extending the existing Medicare program to the entire population. But Medicare today is not comprehensive, cost-free insurance. It includes premiums, deductibles and copayments, excludes certain services, and accommodates private insurance through Medicare Advantage, prescription drug plans and supplemental coverage. Proposals commonly described as Medicare for All would instead establish a fundamentally different system: a federally financed single-payer insurance program offering substantially broader benefits, eliminating most patient cost sharing, and largely displacing private insurance for covered services.
There is another fundamental difference. The existing Medicare program operates within a mixed system of public and private reimbursement. Hospitals and medical providers must recover both the variable costs of treating patients and the fixed costs of maintaining facilities, equipment, staffing and other resources. A hospital with unused capacity may find it worthwhile to treat an additional Medicare patient when the reimbursement covers the marginal cost of treatment, even if that payment does not cover a proportionate share of fixed costs. Higher payments from privately insured patients can help sustain the institution as a whole.
A reimbursement rate adequate for treating an additional patient is not necessarily sufficient to maintain the entire medical system over time. If essentially all medical services were reimbursed at existing Medicare rates, providers would lose the higher payments they currently receive from private insurers. Unless reimbursement rates or operating costs were adjusted sufficiently, some providers would reduce services, defer investment or leave the market. The consequences could include shortages, waiting periods and other forms of rationing. The current Medicare reimbursement structure therefore cannot simply be extended to the entire population with an expectation that it will produce the same results.
Some argue that Medicare already determines private medical prices because private insurers often express reimbursement schedules as multiples of Medicare rates. But using a price schedule as a reference is not the same as accepting its prices. For example, an insurer might negotiate payment for an appendectomy at 1.4 times the corresponding Medicare rate and for cataract surgery at 1.7 times that rate. These illustrative multiples can vary substantially across services, providers and markets, and many private reimbursement arrangements do not rely directly on Medicare rates at all. Medicare may supply a convenient benchmark, but the prices actually paid by private insurers remain the result of separate decisions and negotiations.
For all these reasons, Medicare for All is not simply Medicare without an age restriction. Whatever its merits, its advocates should describe it more accurately as a government single-payer health insurance plan and defend it on that basis.
CIVPAC supports universal health insurance. There are compelling moral and economic reasons to ensure that everyone can obtain necessary medical care. Serious illness can impose catastrophic financial costs, untreated medical conditions can impair productivity and employability, and society is understandably unwilling to deny urgently needed medical treatment to those unable to pay. Providing insurance coverage in advance is generally preferable to addressing these problems after they become emergencies.
But universal health insurance does not require a single-payer system. CIVPAC favors achieving universal coverage through competing private insurers, substantial public subsidies, guaranteed acceptance regardless of preexisting conditions, an enforceable requirement to maintain insurance, and statutory limits, in real per-capita terms, on federal expenditures under the programs described in our proposal below.
The Economic Problems with Single-Payer Insurance
Proposals for government single-payer insurance generally envision the federal government becoming the principal insurer for virtually all Americans, replacing most existing private insurance for covered services. Physicians and hospitals would largely remain independent, but reimbursement rates, covered benefits and much of the financing would become federal responsibilities.
The most important objections are economic rather than ideological.
Fiscal responsibility. A national single-payer system would transfer enormous existing private expenditures to the federal budget. This would not necessarily increase total national health spending by an equivalent amount, since taxes would replace insurance premiums and other private payments. Nevertheless, raising the required revenue would have substantial economic consequences to the extent that the taxes distort economic incentives. Moreover, unless limits were imposed, the government’s financial obligation would increase with the cost and scope of medical care covered.
Prices and resource allocation. A single payer would have considerable bargaining power over medical providers. This might lower prices, but it would also concentrate decisions about reimbursement, medical investment and the allocation of scarce resources in government institutions. Administratively determined prices can be set too high or too low, potentially producing either unnecessary expenditures or shortages. Competition and decentralized pricing are imperfect mechanisms, but they provide information and incentives that a centrally financed system must somehow replace.
Government can perform valuable functions, particularly where markets fail, but there is little reason to presume that it will generally operate more efficiently than competitive private enterprises. The profit motive provides a powerful incentive to reduce costs, improve services, adopt new technologies and discover more efficient ways of operating. Private firms that identify successful innovations can benefit financially, while competitive pressures penalize those that fail to adapt. These incentives are especially valuable in a complex industry where no central authority can anticipate every opportunity for improvement.
Moral hazard. Eliminating most deductibles and copayments would reduce patients’ incentives to consider costs when seeking treatment. This would increase demand for medical services, including some whose benefits do not justify their costs. Cost sharing can also discourage valuable care, so it must be structured carefully. Judiciously designed deductibles and copayments can preserve incentives for restraint without imposing unreasonable financial barriers to necessary treatment.
Making medical services essentially free to patients shifts more responsibility for controlling utilization to insurers, medical providers and government agencies. Patients do not need to be medical experts to have meaningful preferences concerning their treatment. Consumers routinely make decisions about complex products, including automobiles and houses, without fully understanding their engineering or construction. Medical expertise is indispensable in evaluating treatment options, but it cannot tell us how much an individual values the benefits, inconvenience, risks and costs of a particular treatment. Appropriately designed cost sharing allows these individual valuations to influence medical decisions rather than leaving them entirely to insurers, providers or government agencies. Because willingness to pay also depends on ability to pay, adequate subsidies and protection against catastrophic expenses remain essential.
Political incentives. Decisions about covered services and reimbursement would increasingly become political decisions. Patients, medical providers and pharmaceutical companies would have strong incentives to seek more generous benefits and payments. No system can provide every potentially beneficial treatment regardless of cost. A single-payer system does not eliminate rationing; it changes the mechanisms through which rationing occurs.
Transition costs. Replacing most private insurance with a national program would require a massive restructuring of financing arrangements for patients, employers, insurers and medical providers. Even if a new system could eventually operate more efficiently, the transition would entail considerable expense, uncertainty and disruption.
Why American Health Care Costs More
Advocates of a government single-payer health insurance plan correctly observe that the United States spends substantially more on health care than other wealthy countries, without consistently achieving better health outcomes. But higher expenditures do not necessarily indicate inefficiency. Some may reflect the consequences of choices Americans have made about compensation, technology, medical treatment and the quality of facilities and services. Others reflect genuine problems that deserve attention. To the extent that higher costs are a problem, their existence does not establish that single-payer insurance is the best solution.
International spending differences have several identifiable causes.
Pharmaceutical prices. Americans pay substantially higher prices for many patented drugs, including expensive treatments administered in hospitals. American patients consequently provide a disproportionate share of the revenues, and therefore the financial incentives, supporting worldwide pharmaceutical innovation. This raises important questions about international burden-sharing. Importation, international reference pricing, stronger competition from generics and biosimilars, and efforts to secure greater contributions from other wealthy countries could reduce American costs while preserving incentives to develop new treatments.
Higher labor costs. American physicians, nurses and many other skilled medical workers receive substantially higher compensation than their counterparts abroad. Some of this reflects generally higher compensation for highly skilled professionals in the United States. These costs cannot simply be eliminated without affecting the supply and quality of medical labor. Nor should higher compensation automatically be regarded as an inefficiency merely because workers in other countries earn less.
Hospital market power. Hospital consolidation has substantially reduced competition in many American markets. Hospitals with substantial market power can negotiate prices well above those necessary to cover efficient operating costs. This is fundamentally a competition-policy problem. Stronger antitrust enforcement, scrutiny of hospital acquisitions of physician practices, and restrictions on anticompetitive contracts offer alternatives to replacing the insurance system.
Where effective competition cannot be restored, targeted price regulation might be appropriate. Oregon provides an example. The state has limited payments by its public employee health insurance plans to specified multiples of Medicare reimbursement rates, with exceptions for certain hospitals. Research has found that these limits produced significant savings without evidence of corresponding increases in prices charged to other commercially insured patients. Such targeted intervention offers an alternative to wholesale government control of medical reimbursement, although its effectiveness and administrative costs would need to be evaluated in other settings.
Administrative costs. America’s fragmented insurance arrangements impose substantial administrative costs on insurers and medical providers. These costs are a legitimate argument for reform. However, administrative simplification does not require a single national insurer. Standardized billing, more uniform insurance contracts, interoperable information systems and simplified claims procedures could significantly reduce duplication while preserving competing insurance plans.
The appropriate role for government would generally be to facilitate cooperation among insurers, medical providers and technology companies in developing common standards, rather than imposing uniform procedures by regulation. Government could convene industry participants, encourage voluntary agreements and provide financial incentives to adopt more efficient systems.
There are precedents for this approach in other industries. The National Institute of Standards and Technology (NIST) has facilitated industry cooperation on smart-grid interoperability standards and developed a widely adopted voluntary cybersecurity framework in consultation with private organizations. Similar cooperation in health insurance administration could reduce unnecessary costs while preserving opportunities for individual firms to innovate and compete. Such cooperation should address common technical and administrative standards, not the coordination of insurance premiums or other competitive decisions.
Insurers would retain the financial incentives to discover and implement further efficiencies, rather than depending upon government agencies to identify and mandate improvements.
Other costs. Differences in medical technology, treatment intensity, patient health, facilities and other inputs also contribute to spending differences. Some expenditures, such as those associated with better staffing or private hospital rooms, may produce improvements in patient outcomes. Higher costs should be evaluated against the benefits they provide rather than automatically classified as inefficiencies.
Medical malpractice liability may also contribute to American costs, particularly through defensive medicine. Although direct malpractice insurance premiums and claims account for a relatively small share of total expenditures, the possibility of litigation can encourage additional tests, consultations and procedures. Reforms that reduce unnecessary defensive medicine while preserving appropriate compensation for patients injured by medical negligence deserve consideration.
These explanations overlap, and existing research does not permit a precise allocation of the entire international spending difference among them. The appropriate objective is to identify the sources of cost differences and correct their underlying causes where they reflect a genuine problem, rather than simply a difference between the United States and other countries.
It makes more sense to address identifiable problems with targeted solutions than to assume that replacing the existing health insurance system will resolve them.
CIVPAC believes that universal health insurance, meaningful market incentives and fiscal discipline can be combined. The following proposal outlines how.
The Proposal
Amend the ACA in the following ways:
1. Set a limit on the annual per capita average cost of the ACA indexed to inflation, e.g. the Consumer Price Index.
2. Annually reset the co-pays, deductibles, premiums, and subsidies in the system so that the per capita average expense of the system does not exceed the specified limit.
3. Reinstate the tax penalty for not having insurance to a level which pushes compliance to at least 98% of the non-elderly. The tax penalty could easily accomplish this if it was set at or above the cost of the least expensive ACA plan.
4. Make the extension of Medicaid, provided under the ACA, universal. This may require that the federal government bear the full expense of the expansion in all states.
5. Make the value of employer-provided health care benefits taxable income to the employee, just like most other employer-provided benefits.
6. Conforming insurance plans would be required to have substantial deductibles and co-pays.
Medicare
1. Set a limit on the annual per capita cost of Medicare indexed to inflation, e.g. the Consumer Price Index.
2. Annually reset the co-pays, deductibles, premiums, and subsidies in the system so that the per capita expense of the system does not exceed the specified limit.
3. Medicare Supplement and Medicare Advantage plans would be required to maintain substantial deductibles and co-pays.
Medicaid
1. Set a limit on the annual per capita cost of Medicaid indexed to inflation, e.g. the Consumer Price Index.
2. Annually reset the compensation to providers and/or the kinds of care covered so that the per capita expense of the system does not exceed the specified limit.
3. Because this portion of the plan does not provide price-based incentives to consumers, care must be rationed bureaucratically.
Controlling Health Care Costs
Because the plans outlined above would put consumers more directly in touch with their medical care expenses through higher deductibles and co-pays, they would begin to exert downward pressure on medical care costs.
How would this Plan be Paid For?
Part of the costs of this plan would be met from the increased revenues from making employer-provided plans taxable. We would expect such plans would eventually disappear. We would also expect that market forces would result in those benefits being replaced with higher direct, taxable, compensation to employees.
How expensive the plan is depends completely on where the various caps are placed and what measure of inflation is used to reset them. At one extreme, if the limits are set very high and the inflation metric is tied to the overall increase in the cost of health care, the system would resemble “free” universal health care because the premiums, co-pays, and deductible could be quite low. At the other extreme, if the caps are set very low and indexed to a conservative estimate of inflation, like the chain index of consumer prices, the system might have very little cost to the taxpayer, with most of the cost borne by consumers through high premiums, deductibles, and co-pays.
As long as the cap is set to be constraining to some degree, it would end the open-ended entitlement aspect of the current approach. This Plan would require that insurers provide coverage without regard to pre-existing conditions. It would also provide market-based incentives for controlling costs.
Other Similar Proposals
Although CIVPAC developed this proposal independently, it falls within a well-established tradition of market-oriented health reform. Alain Enthoven’s concept of managed competition envisioned broad coverage through competing private health plans, with subsidies adjusted for financial and medical need and consumers facing the additional cost of choosing more expensive coverage. The bipartisan Wyden–Bennett Healthy Americans Act similarly proposed coverage through competing private plans, income-related subsidies, and a requirement that individuals purchase insurance; CBO described its basic structure as requiring individuals to obtain private coverage while providing purchasing pools and federal subsidies to make that requirement workable. CIVPAC likewise believes that guaranteed issue must be accompanied by a meaningful and enforceable mandate to maintain insurance coverage. Otherwise individuals have an incentive to remain uninsured while healthy and purchase coverage only after they become sick.
CIVPAC’s proposal shares this managed-competition philosophy but makes the budget constraint especially explicit. Government would guarantee access to competing private insurance plans and provide income- and risk-adjusted assistance, while placing a statutory limit on the total implied federal subsidy per person. Premium subsidies and mandated benefits would then have to be reconciled with that limit. The objective is universal access through predominantly private insurance, with a genuine obligation to participate, but without creating an open-ended federal commitment whose cost automatically rises with the cost of medical care.
Conclusion
We believe that this plan would capture the efficiency benefits of a market-based approach and provide a minimum level of care to all Americans without saddling the economy with an unsustainable, open-ended entitlement program.
This approach is similar to successful systems in Switzerland and the Netherlands, which use regulated private insurance markets with guaranteed issue, income-based subsidies, and meaningful cost-sharing to achieve near-universal coverage while controlling costs through competition and consumer incentives.
Go to the Table of Contents or to the Next Policy Position
Ready to weigh in? At this stage, each vote has a meaningful impact—see the current results after voting.
Your input helps us refine these policy positions.